
Nashville Judge Halts Tennessee’s Push for Immigration Checks in HIV/AIDS Program
A Nashville judge on Wednesday extended a block on Tennessee’s demand that providers of life-saving HIV/AIDS services check the immigration status of their patients, a move that has thrown a lifeline to hundreds of people living with the disease. Chancellor I’Ashea Myles continued a temporary restraining order, first issued on Oct. 21, that prevents the state from imposing these checks until at least next week, according to reporting from TennesseeLookout.com. The order protects two critical federal programs: the Ryan White HIV/AIDS Program and its companion, Housing Opportunities for People with AIDS (HOPWA).
The Core of the Conflict
At the heart of the legal battle is a new state law, effective Oct. 1, that requires anyone seeking public benefits to prove they are lawfully present in the United States. The law also includes criminal penalties for employees who fail to verify patient status. The Tennessee Department of Health moved swiftly, sending memos to providers like Nashville CARES—a major service organization—demanding they amend their contracts to include these immigration checks.
Nashville CARES saw this as a direct threat to its patients and sued, arguing the mandate violates both federal law and the very purpose of the programs. Represented by the Tennessee Justice Center, the organization’s attorney, Brant Harrell, argued in a four-hour hearing that the state’s actions are “contrary to the public health goal of the programs.” He pointed out a stark admission from the state itself: “The department makes no attempt to deny increased transmission of disease,” Harrell said. “The department’s actions endanger public health. That’s not disputed by the department.”
These programs have been the cornerstone of the U.S. government’s response to HIV/AIDS for over 30 years, providing funding to every state to serve low-income individuals. Federal law explicitly exempts such programs from immigration status checks to ensure people are not deterred from seeking treatment for a communicable disease.
The State’s Defense: A Contract Dispute?
The Tennessee Department of Health, however, painted a different picture. Assistant Attorney General Andrew Grams argued this is not a public health issue but a simple “contract dispute.” He claimed the state was not forcing providers to amend their contracts but merely “making offers” and “giving the options.” Grams made it clear that the Health Department intends to impose these checks with or without the cooperation of local agencies. “At the end of the day, if a recipient refuses, the department has to do verification,” he stated.
This position is complicated by the fact that several other Tennessee agencies have already agreed to update their contracts to include the immigration verification requirements. The state’s scope appears to be widening, as Grams noted that “the department has many, many other programs it is working through” with similar demands. The state also asked the court to require Nashville CARES to post a $450,000 bond if an injunction is granted, a move that shows the high stakes of the legal fight.
The Human and Economic Stakes
The practical impact of this policy is immense. Nashville CARES warned in its legal filings that hundreds of its patients would be at risk of losing not just medical care and prescription drugs but also critical support services. This includes financial assistance that helps pay for private health insurance, a lifeline for many low-income individuals managing a chronic, expensive condition. The demand for documentation creates an immediate barrier for anyone who cannot easily prove their status, forcing a choice between seeking life-saving care and risking legal exposure.
The situation raises a key question of timing and intent. Harrell pointed out that the language the state is enforcing has actually been on the books in Tennessee for 14 years. The difference now is the 2026 law, which adds provisions for reporting individuals who cannot verify their status to a state immigration enforcement division and introduces criminal penalties. This has led to speculation about why the state is suddenly enforcing a dormant provision, especially when, as Harrell noted, “the second Trump administration has imposed no such requirements.”
“The department makes no attempt to deny increased transmission of disease,” as a result of the new directive, Harrell said. “The department’s actions endanger public health. That’s not disputed by the department.”
While the state frames this as an administrative matter, the potential public health consequences are severe. Public health experts widely agree that encouraging testing and treatment for HIV is critical to reducing transmission rates. Policies that discourage individuals from seeking care out of fear can lead to more people being undiagnosed and unknowingly spreading the virus, undermining decades of progress in combating the epidemic.
Chancellor Myles to Rule Next Week
Chancellor Myles is now tasked with a difficult decision. She has scheduled a hearing for Nov. 4 and indicated she will rule by next week on whether to issue a more permanent injunction, effectively stopping the state’s policy while the lawsuit proceeds. Her temporary restraining order is currently broad, applying to all organizations that contract with the state to provide Ryan White services and blocking any effort to require immigration status verification for both current and new applicants.
For now, the block provides a crucial reprieve. It allows Nashville CARES and other providers to continue their work without the immediate threat of losing state funding or being forced into a position that conflicts with their mission and federal guidelines. The outcome of Myles’s final decision will likely have far-reaching implications, not just for HIV/AIDS care in Tennessee but for the future of how other public health programs handle immigration status across the country. The fundamental question remains: should a state’s immigration enforcement goals supersede the federal government’s public health strategy in a decades-old safety-net program?

Wyoming’s wettest November since 1895 was in 1942, Stacker says
November 1942 holds the record for the most precipitation in Wyoming since 1895, according to data compiled by...

Seattle Voters Approve Proposition 1 to Raise Sales Tax for Public Transit
Seattle Voters Double Down on Transit Tax with 73% Approval Seattle voters have given a resounding thumbs-up to...
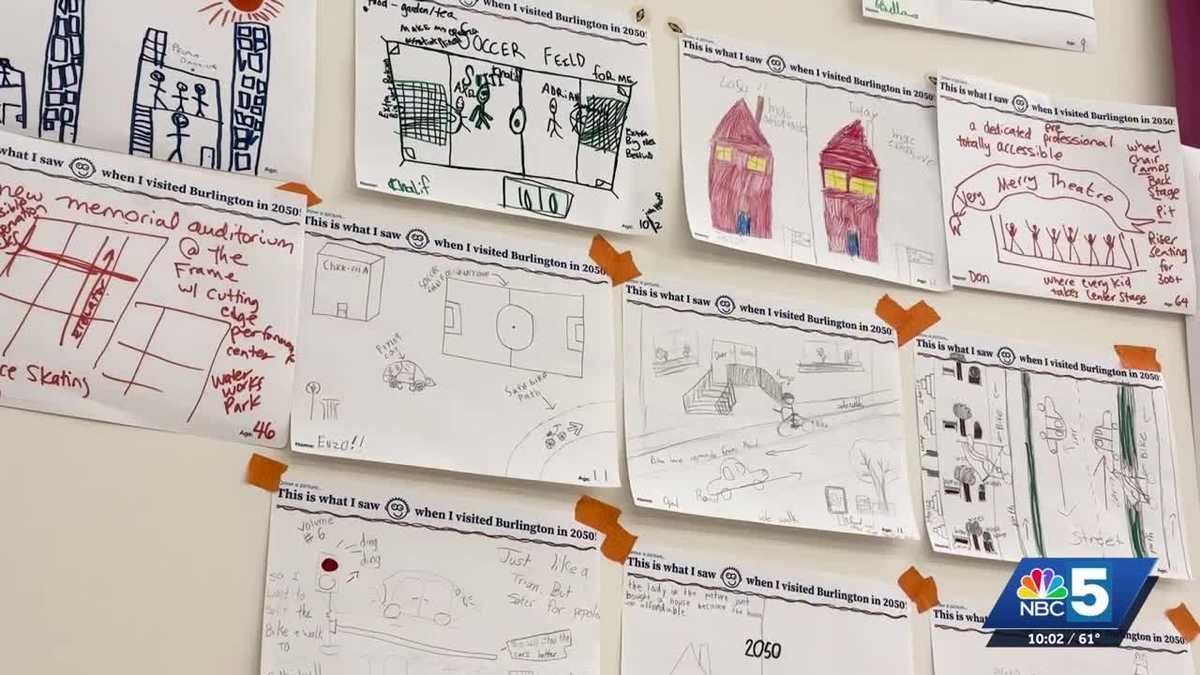
Burlington holds public forum on PlanBTV2050 development
Burlington's Future Hangs in the Balance "That's one of the key questions we're asking tonight, given the capacity...

Vikki Goodwin Wins Texas Lieutenant Governor Election to End GOP Era
Vikki Goodwin has been elected as the lieutenant governor of Texas, becoming the first Democrat to win the...