
Posterior reversible encephalopathy syndrome, a rare neurotoxic state marked by encephalopathy and vasogenic edema, can mimic acute ischemic stroke and complicate severe autoimmune disorders, requiring careful neuroimaging and blood pressure management to achieve neurological recovery.
Evolution of Diagnostic Criteria and Terminology Since 1996
Back in 1996, Hinchey et al. introduced the term reversible posterior leukoencephalopathy syndrome
to characterize the initial neurological presentation of 15 patients experiencing headache, seizure/status epilepticus, confusion, lethargy, vomiting, and diminished eyesight. Two years later, Dillon et al. proposed the term reversible posterior cerebral edema syndrome
, underscoring vasogenic edema as a core feature of this disorder. Subsequently, in the year 2000, the term posterior reversible encephalopathy syndrome (PRES)
emerged in a study by Casey et al., who advocated for fluid-attenuated inversion recovery (FLAIR)—a magnetic resonance imaging (MRI) method—as the preferred diagnostic approach. In 2002, Schwartz et al. categorized this disorder as a form of hyperperfusion encephalopathy
, thereby providing a leading mechanistic hypothesis.
While early studies focused heavily on the pathogenic role of hypertension and hyperperfusion, more recent investigations have examined the role of immune activation.
As a clinical syndrome, posterior reversible encephalopathy syndrome represents a confluence of multiple contributing factors that includes hypertension, immune activation, renal dysfunction or failure, and preeclampsia or eclampsia. Specific treatments for the syndrome are lacking, meaning that symptom management with the use of anti-hypertensive or anti-seizure therapeutics, along with the elimination of precipitating causes, serves as the mainstay of clinical care.
Dual Neurological Syndromes in Late Postpartum Eclampsia
Medical literature documents complex presentations involving concurrent autoimmune conditions and eclampsia.
Severe Autoimmune Hyperthyroidism and Cortical Visual Loss Mimicking Stroke
Severe thyrotoxicosis and systemic metabolic stress can also trigger posterior cerebral abnormalities. A documented case describes a patient with severe autoimmune hyperthyroidism who developed acute encephalopathy, recurrent focal and generalized seizures, and profound bilateral visual impairment. The initial occipital MRI abnormality was interpreted as a posterior cerebral artery territory infarction, prompting initial treatment considerations for acute ischemic stroke before interval improvement supported the correct diagnosis of posterior reversible encephalopathy syndrome.
The accumulation of fluid inside brain tissue resulting from heightened permeability of the blood-brain barrier is known as vasogenic edema. The syndrome is believed to arise from a combination of impaired cerebral autoregulation and endothelial dysfunction, resulting in blood-brain barrier disruption and predominantly vasogenic cerebral edema, with severe hypertension acting as an important precipitant even though it is not present in all cases.
Multisystem Autoimmune History and Blood Pressure Management
Diagnostic hurdles are compounded when patients present with extensive overlapping medical histories. Upon her readmission, she suffered from leukocytosis, encephalopathy, and a hypertensive crisis, while initial scans pointed toward subacute infarction; however, subsequent brain MRI showed bilateral posterior hyperintensities that aligned with posterior reversible encephalopathy syndrome.
Endothelial activation, compromised blood-brain barrier integrity, and cerebral hypoperfusion can be incited by inflammatory cytokines, circulating toxins, sepsis, renal failure, and autoimmune disease, which accounts for cases linked to systemic inflammatory states, immunosuppressants, and cytotoxic agents. Her marked hypertension—with systolic pressures persistently above 180 mmHg on presentation—is consistent with the approximately 80% of patients who present with acute hypertension. Managing her blood pressure successfully led to clinical and radiological improvement, which points to the hyperperfusion mechanism as the primary driver in her situation, alongside a clinical course complicated by recurrent respiratory failure requiring re-intubation, systemic inflammatory response without proven infection, and severe treatment-resistant hypertension.
Practical Next Steps
Readers concerned about neurological symptoms, blood pressure complications, or autoimmune disorders should consult qualified medical professionals for proper evaluation and personalized guidance rather than relying on general overviews.
Worth a look

Troponin Elevation in 20.4% of NSTE-ACS Patients
Out of 481 patients with non–ST-segment elevation acute coronary syndrome, 98 individuals—representing 20.4% of the cohort—met angiographic criteria...

Nitrous Oxide Abuse Linked to Rhabdomyolysis and AKI
A 22-year-old man developed severe rhabdomyolysis.
Ebola Outbreaks Linked to Distant Macroclimatic Shifts by Study
Distant macroclimatic oscillations modify continental rainfall and alter ecological conditions to create seasonal windows that trigger Ebola virus...
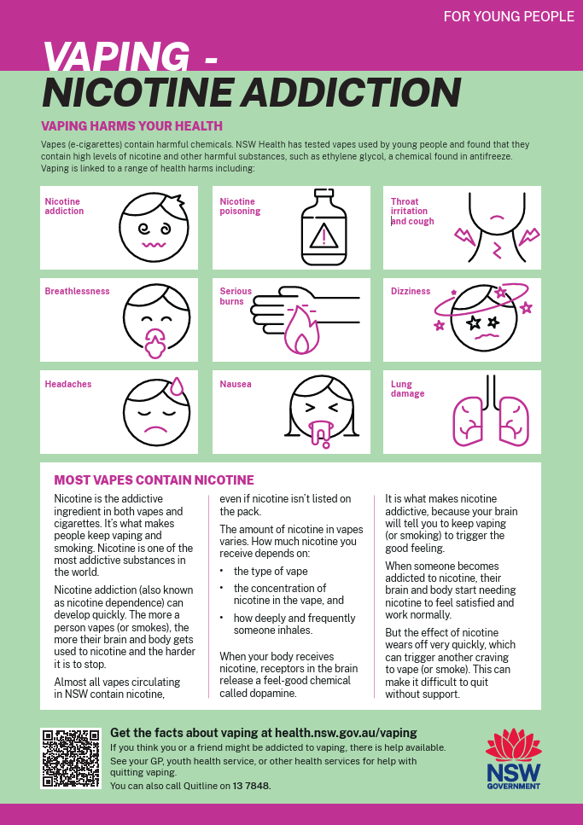
High-Nicotine Vapes Linked to Greater Nicotine Dependence in Young Adults
Between 2017 and 2022, high-nicotine e-cigarette use surged nearly 80 percent among young adults aged 18 to 24...